

Someone has looked under your baby’s tongue and said, “That could be a tongue-tie.” If feeding is painful, slow or stressful, the label can feel like an explanation and a treatment plan at the same time. It is neither on its own.
The useful question is not simply whether a band of tissue is visible. It is whether that tissue restricts your baby’s tongue movement enough to cause a specific feeding problem. A careful decision connects what the mouth looks like, how the tongue moves and what actually happens during feeds.
A diagnosis has to connect anatomy to function
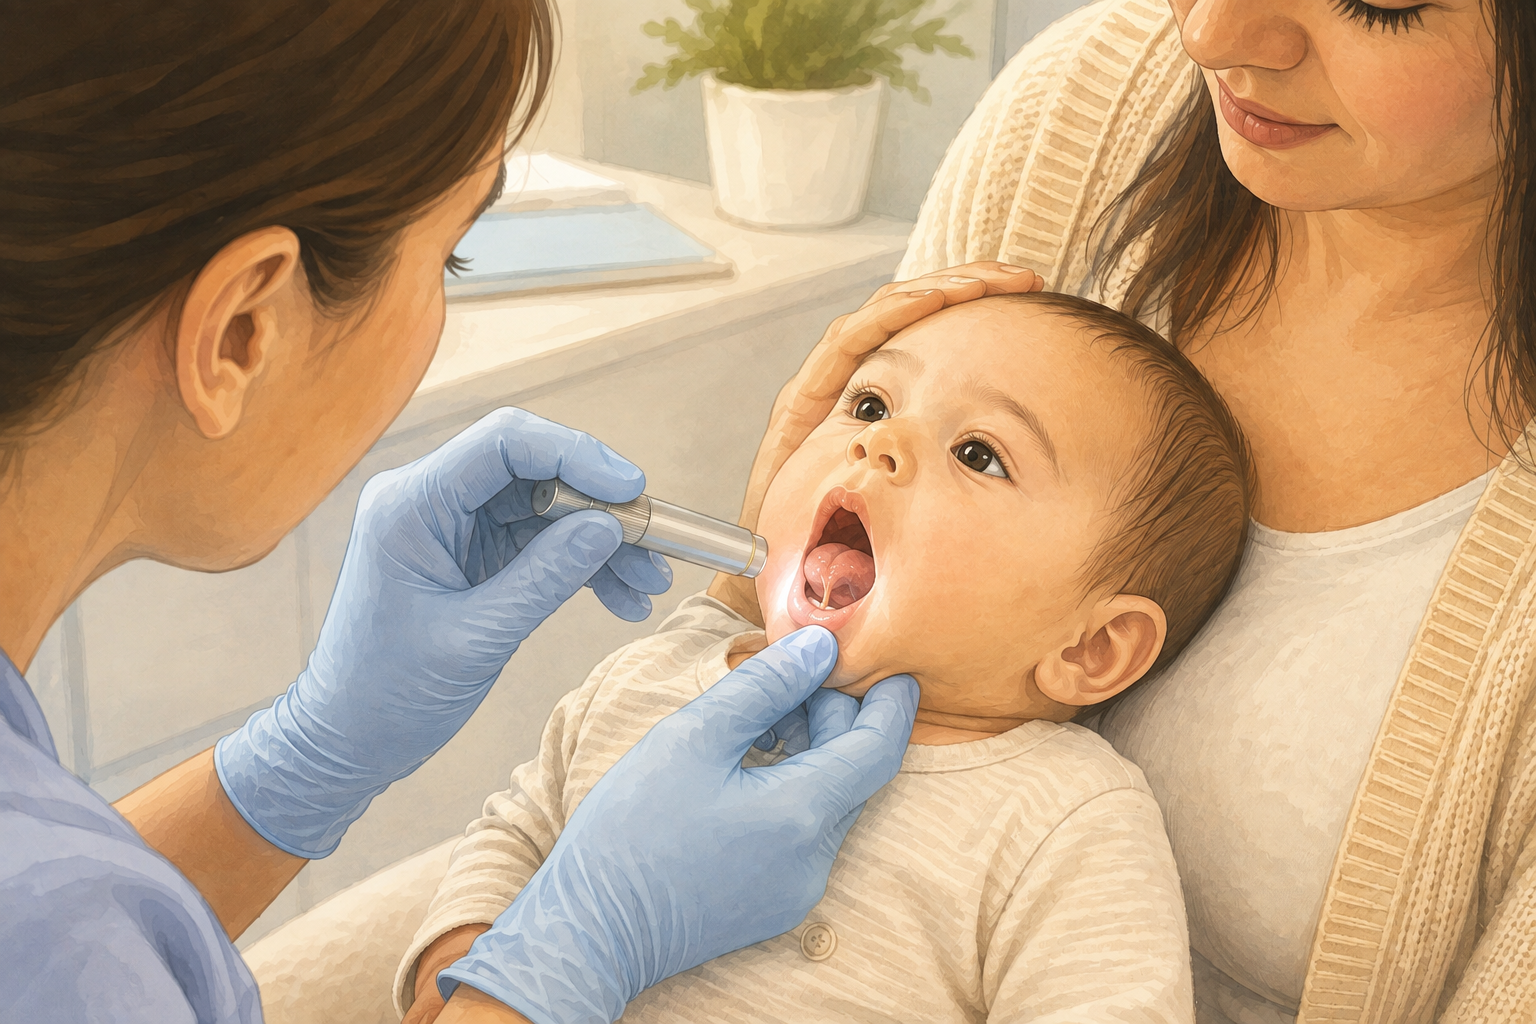
The lingual frenulum is the tissue joining the underside of the tongue to the floor of the mouth. Tongue-tie, also called ankyloglossia, describes a frenulum that restricts useful tongue movement. The important word is restricts. A visible, short-looking or prominent frenulum does not prove that it is interfering with feeding.
The concern about tongue-tie being overdiagnosed arises when common breastfeeding difficulties are treated as proof of a tie without establishing that restricted tongue movement is their cause. Breastfeeding can be difficult for many reasons, and more than one factor can be present at the same time.
A useful assessment should answer three separate questions:
- Anatomy: Is there a frenulum that appears unusually restrictive?
- Movement: Which movement can the baby not perform effectively, such as lifting or extending the tongue or maintaining a seal?
- Consequence: How is that restriction affecting milk transfer, attachment, parental pain or the baby’s growth and hydration?
If the explanation stops at “the frenulum looks tight,” ask how its appearance relates to the feeding problem you are seeing. Appearance can support a diagnosis, but function should drive the decision.
Record the feeding problem before the appointment
You do not need to diagnose tongue-tie at home. You can, however, bring much better information to the assessment. Observe several typical feeds rather than relying on one especially difficult or unusually calm feed.
Write down what you notice in these areas:
- Attachment: Does your baby attach deeply and stay attached, or repeatedly slip off and need to relatch?
- Seal: Do you regularly hear clicking or notice milk leaking from the mouth? These can signal a poor seal, but they do not identify its cause.
- Swallowing: Can you see or hear active swallowing, or does the feed seem to involve plenty of sucking with little obvious transfer?
- Comfort: Is breastfeeding painful throughout the feed? Is there nipple compression or damage? Note whether skilled changes to positioning and attachment alter the pain.
- After the feed: Does your baby appear satisfied, or continue showing feeding cues soon after?
- Overall intake: Bring any recent weight records and tell the clinician about changes in wet diapers, stooling, alertness or willingness to feed. What is expected varies with age, so ask for an age-specific medical assessment rather than comparing your baby with a generic online threshold.
- Bottle feeding, if relevant: Note difficulty maintaining the teat, repeated leaking, coughing, distress or feeds that consistently feel ineffective.
None of these signs confirms tongue-tie by itself. Pain can come from attachment difficulties that are unrelated to the frenulum. Clicking can occur with positioning or milk flow issues. An unsettled baby may be reacting to hunger, discomfort or something unrelated to feeding. The pattern matters more than any single sign.
A short video of a typical feed may help if your clinician is willing to review it, but it should supplement rather than replace an observed feeding assessment. Do not pull, stretch or force your baby’s tongue to test its range yourself.
Ask for an observed feed before consenting to a procedure

A mouth examination shows anatomy. An observed breast or bottle feed shows function. When feeding is the reason treatment is being considered, you generally need both.
The medical part of the assessment should consider your baby’s general health, oral anatomy, hydration and growth. The feeding part should look at attachment, positioning, sucking, swallowing, seal and milk transfer. Depending on where you live, this may involve a family doctor or pediatric clinician alongside a lactation or infant-feeding professional. The person proposing a procedure should be able to explain how their finding fits with the feeding assessment.
Other possible contributors should not be dismissed merely because a frenulum is visible. They can include positioning and attachment, milk supply or flow, breast or nipple pain, illness-related sleepiness, prematurity and other oral, airway or neuromuscular difficulties. That does not mean the frenulum is irrelevant. It means the assessment has to identify which factor is doing what.
Use these questions during the appointment:
- What movement is restricted, and how did you assess it?
- How is that restriction causing the feeding problem we are seeing?
- What other causes have been considered?
- Can you observe the kind of feed that is causing difficulty?
- What feeding support can we try, and is it safe to try that before a procedure?
- If a procedure is recommended, what specific improvement should we expect?
- How and when will feeding, weight and healing be reviewed afterward?
- What is the plan if feeding does not improve?
If a procedure is recommended from a photograph or a brief look alone, and your baby is medically stable, it is reasonable to ask for a fuller functional assessment or a second opinion. If intake or hydration is a concern, do not delay medical care while arranging that opinion.
When feeding trouble needs faster medical attention
Tongue-tie discussions should never distract from the immediate issue of whether your baby is getting enough milk and is otherwise well. Contact a pediatric clinician or your local urgent health service promptly if your baby is feeding much less than usual, becoming increasingly sleepy or difficult to wake for feeds, producing noticeably fewer wet diapers than is normal for their age, repeatedly vomiting or showing signs of dehydration.
Breathing difficulty, blue or grey colouring, unresponsiveness or severe weakness requires emergency help. After any oral procedure, bleeding that does not stop, breathing trouble or a baby who cannot feed also needs urgent medical attention.
Treatment should have a clear, measurable target

Not every diagnosed tongue-tie needs to be divided. If your baby feeds effectively, growth and hydration are appropriate, and feeding is comfortable enough for you, the presence of a frenulum alone does not create an automatic need for treatment.
When the main problem is breastfeeding, skilled support with positioning and attachment may be the first useful step. Your baby’s clinician may also recommend an individualized plan for protecting intake and monitoring weight while feeding is being assessed. If expressed milk or supplementation is medically needed, the amount and method should be tailored to your baby’s age and situation rather than taken from general online advice.
Trying appropriate feeding support is not a way to deny that tongue-tie exists. It can improve a separate feeding issue or make the effect of a genuine restriction easier to identify. Support should not become an endless test, however. Persistent pain, ineffective transfer or growth concerns deserve timely reassessment.
A frenotomy releases the restrictive frenulum. It may be considered when a trained clinician has documented restricted movement, that restriction plausibly explains a current feeding problem, and appropriate feeding help has not solved the problem or is not sufficient on its own. This is the kind of situation in which treatment may be appropriate rather than automatic.
A procedure should be tied to an outcome you can assess. Depending on the problem, that might be less nipple pain, a more stable attachment, more effective milk transfer or an improved weight trajectory. Ask when that outcome will be reviewed and what support will be available during the adjustment afterward. Improvement is not guaranteed because the frenulum may not be the only cause of the feeding difficulty.
Frenotomy cuts tissue and is not a risk-free diagnostic experiment. Before consenting, ask the appropriately trained and regulated clinician to explain pain control, bleeding, infection, injury, scarring, healing problems, the possibility that symptoms will persist and whether another procedure could be proposed. Ask what experience the clinician has, how complications are handled and who provides follow-up.
Follow the clinician’s feeding and wound-care instructions after treatment. If exercises are recommended, ask for a clear demonstration, their intended purpose and guidance on what level of discomfort or bleeding means you should stop and seek advice. Do not substitute forceful techniques found online for individualized postoperative care.
Key takeaways
- A visible frenulum is not enough to diagnose a feeding problem. The assessment should connect anatomy, restricted movement and a real functional consequence.
- Repeated attachment problems, clicking, leaking, pain or poor transfer can justify assessment, but none is specific to tongue-tie.
- When feeding is the concern, ask for both an oral examination and an observed feed.
- Feeding support can address other causes and clarify whether restricted tongue movement is still interfering.
- Consider a procedure only with a defined reason, an expected measurable benefit, an explanation of risks and a follow-up plan.
- Poor intake, dehydration, unusual sleepiness or breathing difficulty requires medical attention, regardless of whether tongue-tie is suspected.
At your next appointment, ask the clinician to complete this explanation plainly: the frenulum restricts a particular movement, that restriction causes a particular feeding problem, and treatment is expected to improve a particular outcome. If those links are missing and your baby is medically stable, pause before consenting and seek a fuller assessment. If your baby’s intake or wellbeing is deteriorating, make medical evaluation the first priority.
References




