
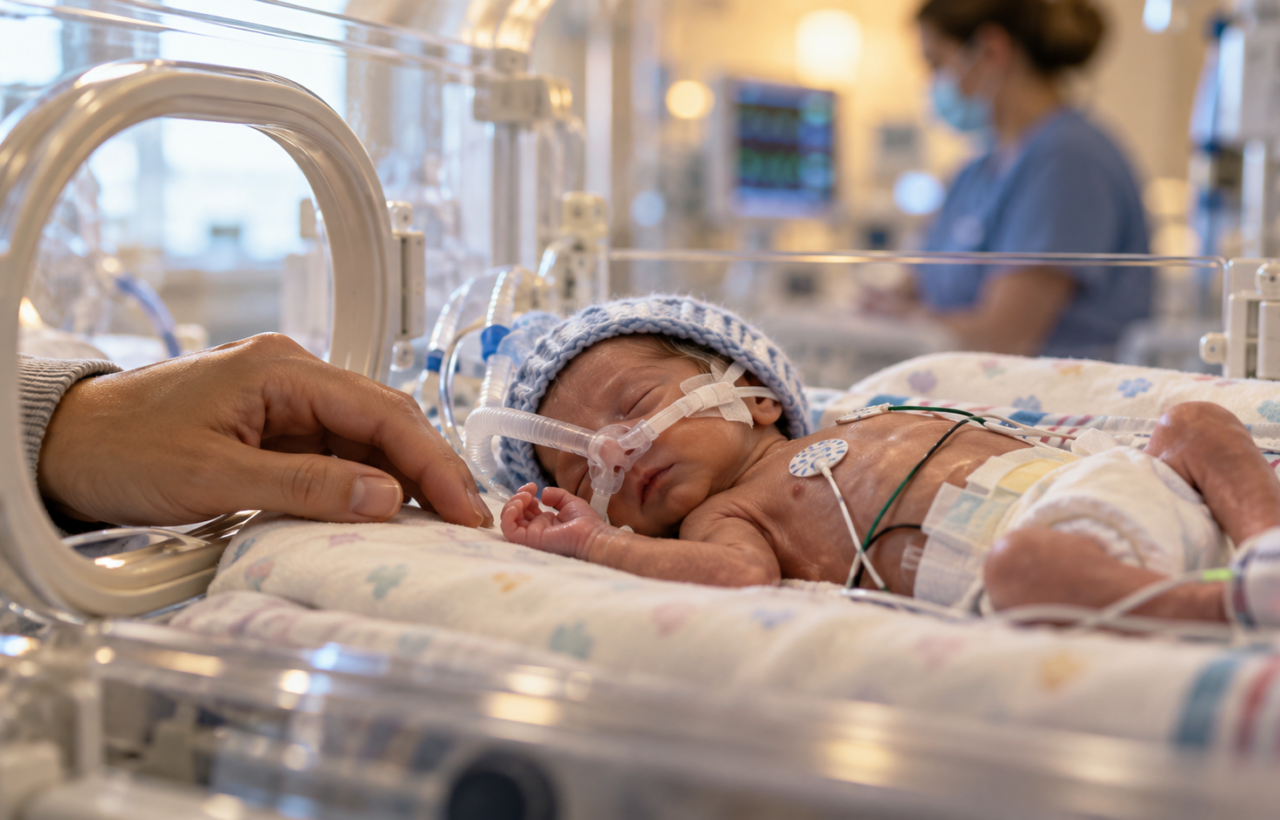
If your baby has arrived far earlier than expected, or an early delivery may be imminent, the question can crowd out everything else: Will my baby survive? The honest answer is that no headline, birth weight, or online percentage can predict what will happen to one baby.
Your obstetric and neonatal teams can give you a more relevant answer because they know your baby’s estimated gestational age, condition, complications, and available care. You can use the questions below to understand that answer, notice when it changes, and make decisions without mistaking either hope or fear for certainty.
Why one survival number cannot answer your question
Survival statistics describe groups of babies. A prognosis applies that group information to the baby in front of the medical team. Those are related, but they are not the same.
Gestational age is usually expressed in completed weeks and days. Birth weight is a separate measurement. Two babies can have the same weight but different gestational ages, growth histories, medical problems, and responses after birth. That is why weight alone cannot settle the question.
The team also considers your baby’s condition at birth, breathing and circulation, signs of infection or other illness, congenital conditions, early complications, and response to treatment. The hospital’s experience and resources matter too. Some of these facts are known immediately; others become clearer as your baby’s course unfolds.
The existence of record-setting survivors born at extraordinarily small sizes shows that survival can be possible in rare circumstances. It does not reveal the odds for another baby who shares only one feature, such as a similar weight. Let those stories make room for possibility, but do not use them as a personal forecast.
When someone gives you a percentage, ask what population it came from and what outcome it measures. Survival through delivery, survival through the newborn period, and survival to hospital discharge are different endpoints. Also ask how your baby’s individual facts move the estimate above or below the group average. A number without those qualifiers can sound more precise than it is.
Turn the prognosis into a conversation you can use

In a stressful conversation, broad questions often produce broad answers. Ask the neonatologist to separate what is known, what is uncertain, and what could change soon. These questions can help:
- What is our baby’s estimated gestational age, and how confident are you in that estimate?
- What outcome do you mean when you use the word survival?
- Which facts about our baby improve the outlook, and which make it more concerning?
- Is this estimate based on general population data, this hospital’s experience, or both?
- What has changed since the previous update?
- What are the best, most likely, and most concerning paths from here?
- What will you watch next, and what finding would change your assessment?
- Is a decision required now? If so, why is it time-sensitive?
Ask the clinician to use plain language, then repeat the explanation back in your own words: This is what we understand; is that right? That is not a test of you. It is a reliable way to expose misunderstandings before they shape a decision.
If different clinicians seem to be giving different answers, ask whether the baby’s condition has changed, whether they are using different outcome definitions, or whether they are interpreting genuine uncertainty differently. Request a family meeting with the relevant teams if major decisions are being discussed. A planned conversation is usually easier to follow than several fragments gathered during busy bedside care.
If the team discusses resuscitation limits, life-sustaining treatment, or comfort-focused care, ask for the medical reasoning behind each option, the likely benefits and burdens, and which parts reflect your family’s goals and values. These are decisions for shared discussion with clinicians who know your baby’s situation. An online story, chart, or general explanation cannot safely make them for you.
Survival and long-term outcome are separate questions

A baby can survive extreme prematurity and still need prolonged hospital care or continuing support. Possible areas of concern include breathing, feeding, growth, hearing, vision, movement, learning, and development. The range is wide, and a possible complication is not a prediction that your baby will have it.
Some long-term outcomes cannot be determined during the first conversations after birth. The baby’s medical course, complications, and development over time add information. Ask the team to distinguish among what is already present, what is merely a risk, and what cannot yet be assessed. Those categories should not be blended together.
When discussing development after discharge, ask whether the team is using chronological age or corrected age. Corrected age accounts for how early a baby was born and can provide a more appropriate frame for early developmental expectations. It does not replace follow-up or explain every difference.
Before discharge, ask who will coordinate follow-up and which services are expected. Depending on the baby’s needs, that plan may involve neonatal follow-up, primary care, feeding support, hearing or vision assessment, rehabilitation, or developmental services. Get the plan in writing, including whom to contact if an appointment does not arrive.
What you can do before birth and in the NICU

You cannot control the medical course, but you can make communication clearer and ask how to participate safely in your baby’s care.
If very early delivery may happen
- Ask to speak with a neonatal clinician before delivery if circumstances allow.
- Ask what level of newborn care the hospital can provide and whether transfer to another centre is being considered. Do not arrange or attempt a transfer yourself; the obstetric and neonatal teams must decide what is medically safe.
- For every treatment proposed before delivery, ask what it is intended to change, what its important risks are, and what happens if there is not enough time to give it.
- Ask what may happen in the delivery room and where you or your support person are likely to be.
- Tell the team if you need an interpreter or cultural, spiritual, or accessibility support. Complex decisions should not depend on a family member informally translating medical details.
Once your baby is in intensive care
- Choose one family contact for clinical updates. That person can share information with others and reduce the strain of repeating it.
- Keep a dated note with the clinician’s name, the main concern, what is supporting the baby, the next checkpoint, and any decision pending. A change in prognosis may otherwise be hard to distinguish from a change in wording.
- Ask when rounds or regular updates occur and how to request a family meeting. If you want to record a conversation, obtain everyone’s permission first.
- Ask which forms of involvement are safe now. Depending on the baby’s condition, the team may be able to guide you in touching, holding, skin-to-skin care, diaper changes, or other care. Wait for bedside approval because stability and equipment needs can change.
- If providing your own milk is something you want to explore, ask early for practical feeding and lactation support. If it is not possible or not right for you, ask the team to explain the available feeding plan without treating feeding choices as a measure of commitment.
- Follow the unit’s infection-control instructions and tell staff promptly if you are unwell or have had a relevant exposure.
Parents often feel they must remain at the bedside continuously to prove they are present. You are still your baby’s parent when you sleep, eat, shower, care for another child, or leave the unit. Ask the social worker or bedside team about lodging, transportation, work documentation, financial support, mental-health care, and help for siblings. Practical strain can interfere with understanding and decision-making, so addressing it is part of getting through the admission.
Key takeaways
- A survival statistic describes a group; it cannot determine one baby’s outcome.
- Gestational age and birth weight are important but not interchangeable, and neither should be interpreted alone.
- Ask what survival endpoint a number describes and which individual factors shift your baby’s prognosis.
- Separate survival, current complications, future risks, and long-term development. They are related questions, not one question.
- When a decision is proposed, ask what is urgent, what remains uncertain, and how the options fit your family’s goals.
- Use the neonatal team that knows your baby’s condition as your primary source for medical decisions.
For your next update, write down three prompts before the clinician arrives: What do you know now? What remains uncertain? What decision, if any, is needed before the next update? Those questions will not remove the uncertainty, but they can turn it into information you can work with.
References




